Anatomy · Physiology · Research
Understanding shoulder pain
Anatomical references, proposed mechanisms and analysis of scientific data.
On this page
Scientific dossier · Separate reading of practical advice
Functional and biomechanical anatomy
The scapular belt combines the gleno-humeral joint, scapula, clavicle and their joints. The tendons of the rotator cap contribute to the control of the humeral head during movements. The elevation of the arm results from coordination of several segments; it is not limited to the passage of a tendon under a bone.
Physiology and mechanisms of symptoms
The tendons may have changes related to age or load, sometimes without pain. Sensitivity, strength and stress tolerance also vary depending on activity and recovery. An image of rupture or tendinopathy must be confronted with clinical history; it does not describe disability alone.

Clinical reasoning and guidance
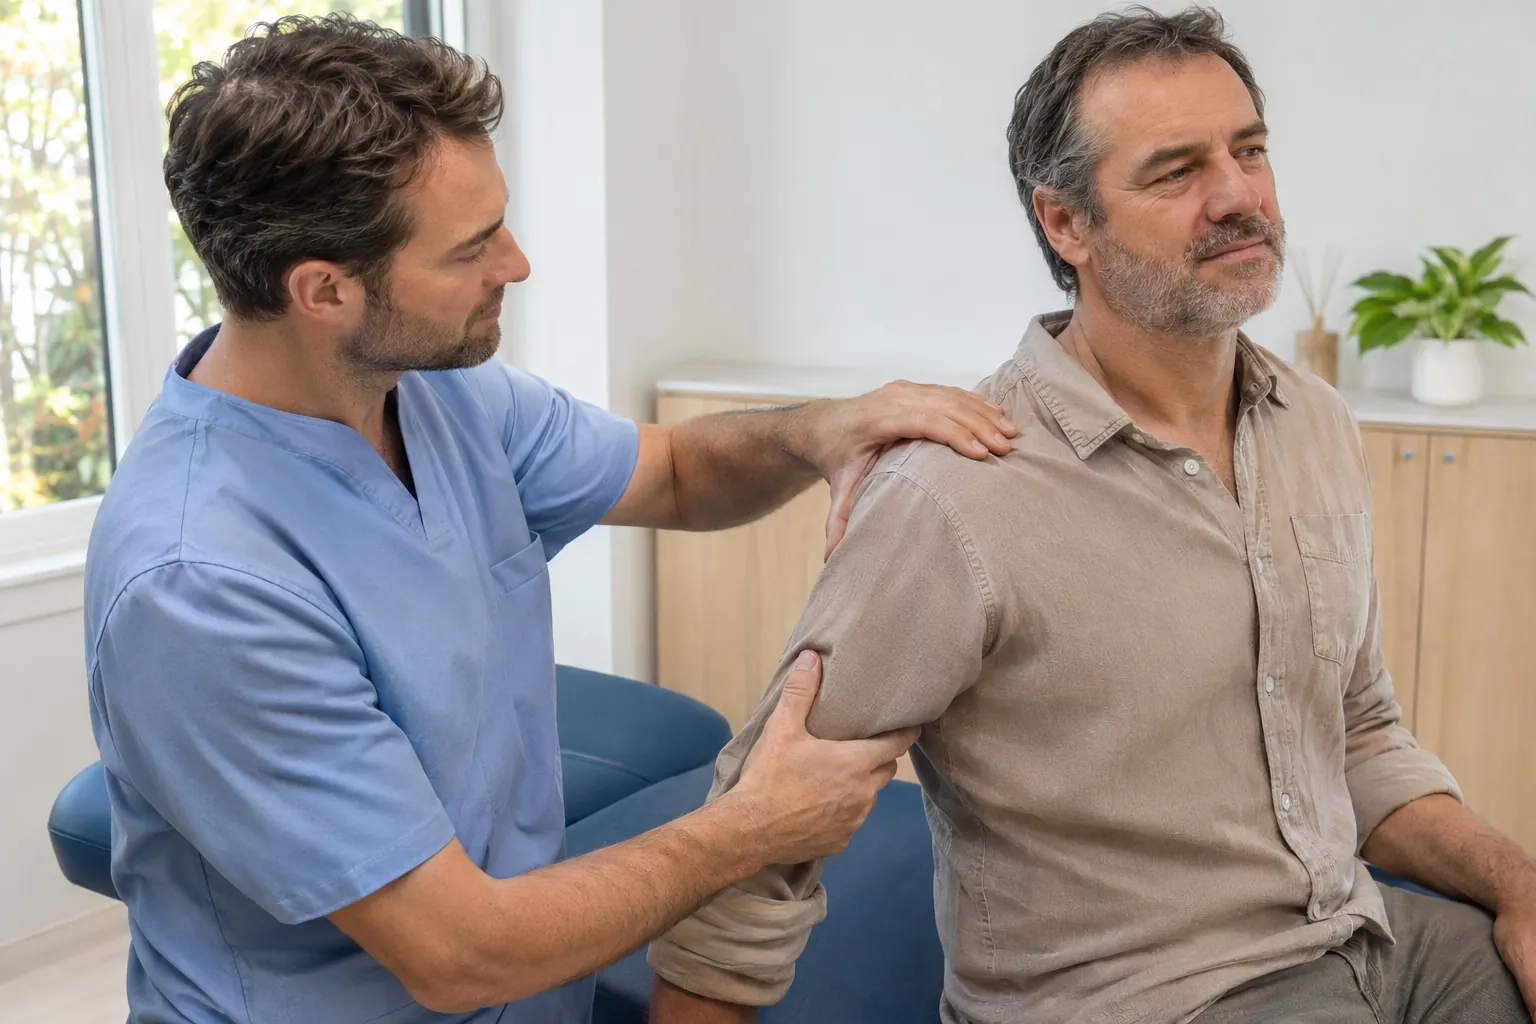
The reasoning distinguishes pain after trauma, severe stiffness, weakness and non-traumatic picture. The examination compares active and passive movements, then searches for items that orient to the neck or other cause. A new disability after falling and general symptoms require medical advice before any attempt at forced mobilization.
Scientific data and recommendations
HAS describes the diagnostic path and medico-functional treatment of non-traumatic pain and tendinopathy. The AAOS recommendations on cap lesions complement international benchmarks. These frameworks support an appropriate assessment; they do not demonstrate the effectiveness of an osteopathic protocol.

What the results do not support
Pain during a test does not identify with certainty a responsible tendon. Expressions of conflict or disentangled shoulder may be misleading if presented as diagnoses based on a single gesture. A transient manual relief does not indicate that a rupture is repaired.
Functional monitoring and coordination of care
Follow-up can include dressing, access to a shelf, sleep and the ability to gradually load the arm. The objective depends on the patient's needs, not the search for an amplitude identical to that of another. A growing stagnation or weakness requires a reassessment of the care path.
Scope of this file
- Population and situation
- Shoulder pain: Lifting the arm becomes difficult. The results must be interpreted for this specific situation.
- Choice of care
- HAS describes the diagnostic path and medico-functional treatment of non-traumatic pain and tendinopathy.
- Security priority
- After a fall with an impossibility to lift the arm, in case of deformation, red and warm joint or pain associated with chest oppression, ask for a quick medical opinion.
The cap does not act in isolation
The tendons of the cap participate in the control of the humeral head during movement, in coordination with the muscles of the scapula and arm. An elevation pain alone does not identify a specific lesion. Strength, active and passive amplitudes, context and evolution provide additional information. Trendy changes observed in imaging should be interpreted with the clinical picture rather than automatically considered as the source of the symptom.
Measure function rather than realignment
Research can examine the intensity of pain, the ability to use the arm and the quality of life. The immediate gain of amplitude after treatment does not prove a tendinous repair. The SAS recommendations frame the evaluation of a pain-free, non-traumatic shoulder and tendinopathy management. Their scope does not extend to an acute traumatic rupture or a suspicion of dislocation, which require a specific decision.
Bibliography and original documents
- HAS · diagnostic path and tendinopathies of the cap
- AAOS · Rotator cuff injuries, recommendations 2025
Editorial and documentary review: November 5, 2026. The references describe their scope; they are not valid for all osteopathic practices.